Ventricular Septal Defect (VSD)
- A defect in the ventricular septum resulting in a communication between the right and left ventricle.
- Common congenital abnormality which occasionally requires surgical intervention.
- Can occur after a myocardial infarction usually to patients presenting late to hospital.
- Classically the smaller the VSD the louder the heart murmur usually best heart at the left lower sternal border and is pansystolic.
Types of VSD
- Subarterial: Least common and associated with aortic insufficiency due to close proximity to the aortic valve.
- Membranous: Most common type of VSD involving the membranous septum and accounting for usually 80% of cases.
- AV canal type.
- Muscular: Second most common type and most likely to close spontaneously.
Characteristics
Often characterized as Restrictive vs non-restrictive and based on the size small, medium and large.
- In Restrictive VSD’s the LV pressure is higher than the RV.
- In non-restrictive RV and LV have similar pressures.
Example 1 Muscular VSD


Parasternal views demonstrating flow accross the ventricular septum.


Apical 4 chamber view demonstrating a clear defect in the septum and colour doppler confirms left to right blood shunting.
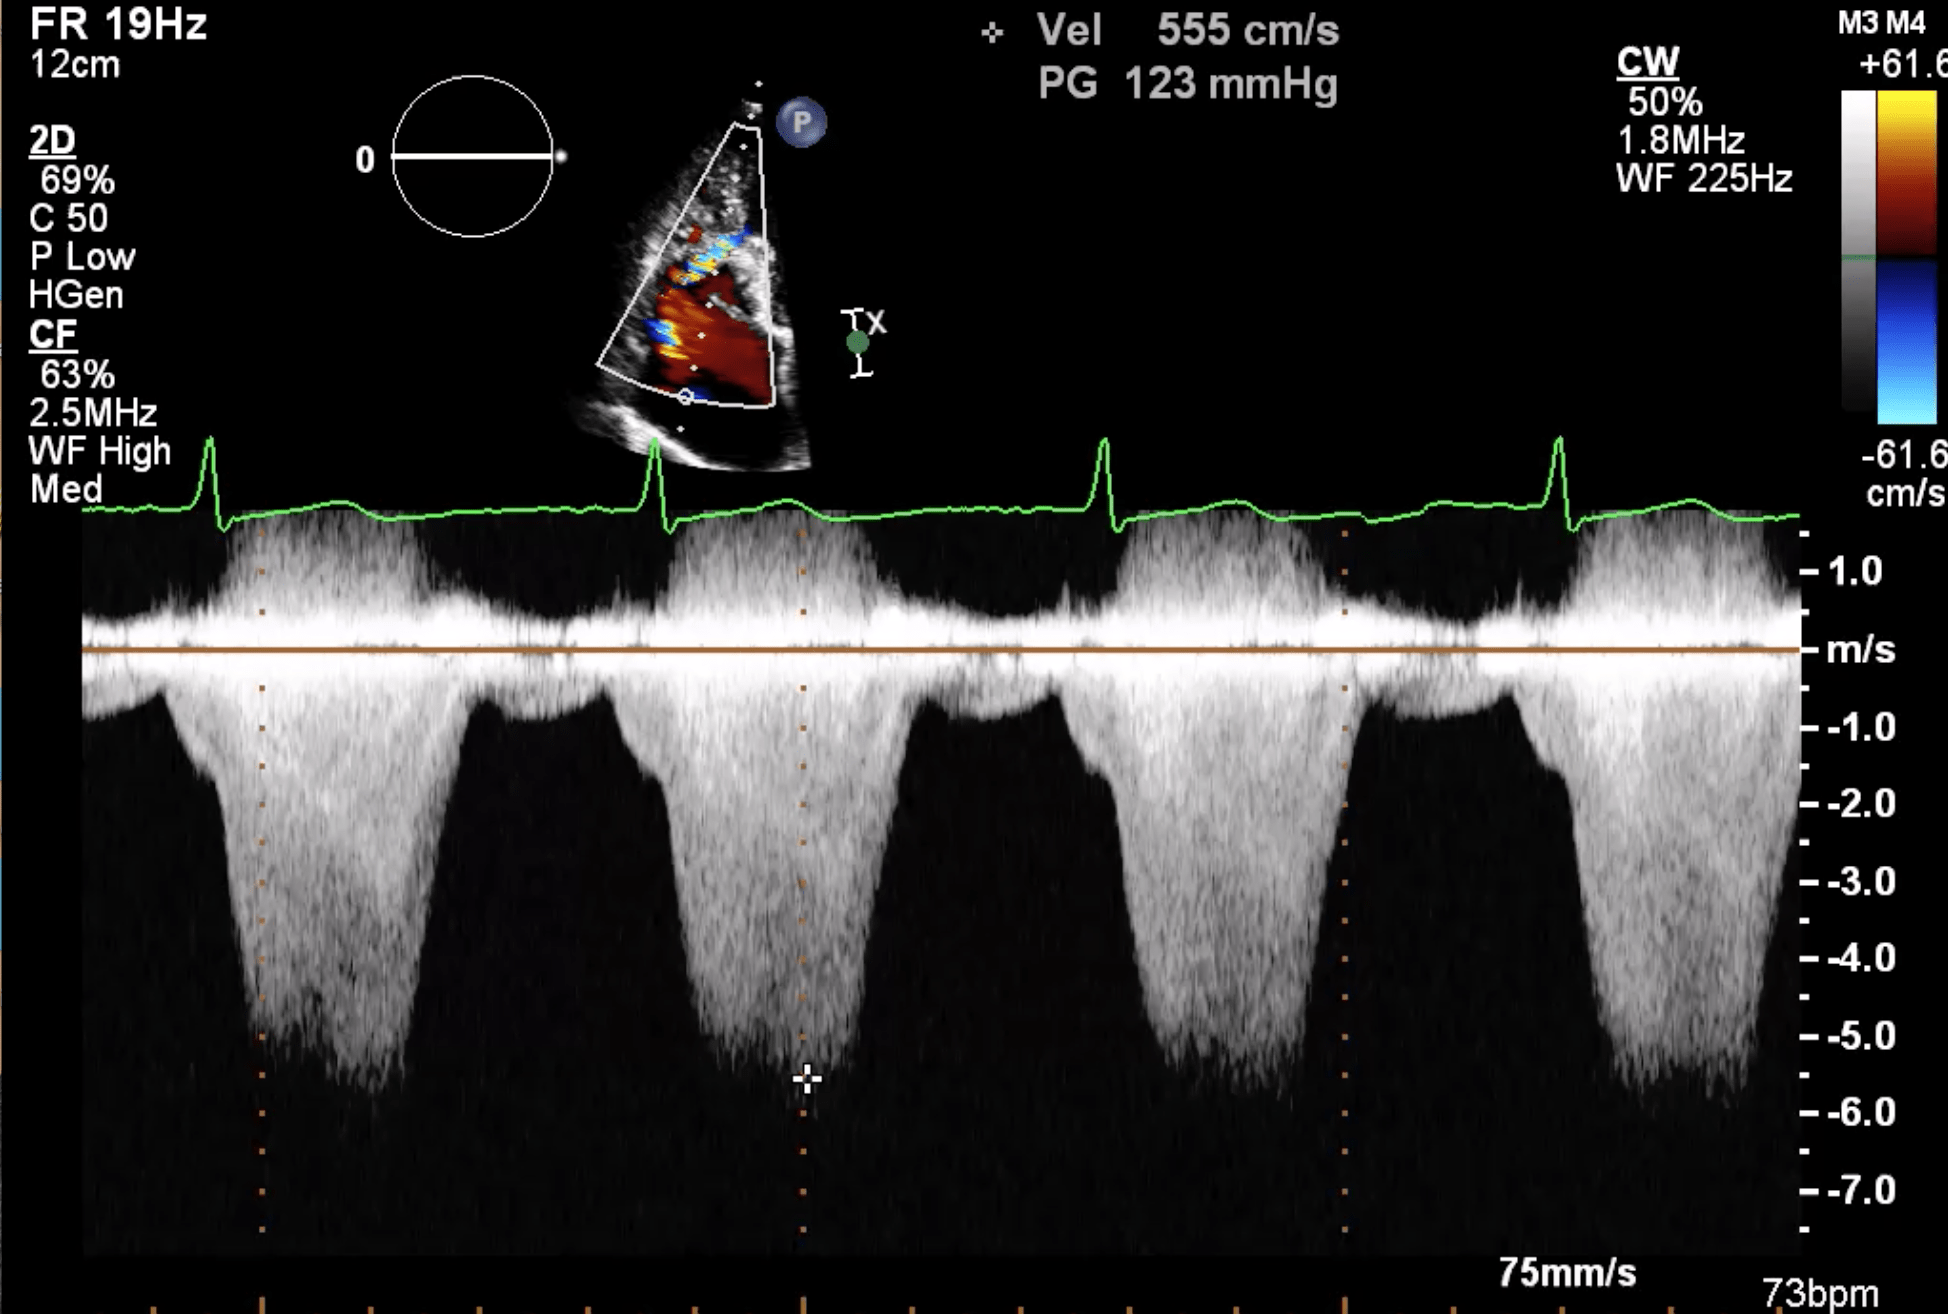
Continuous wave doppler across the VSD demonstrating the peak gradient.
Example 2 Membranous VSD
- Parasternal long axis view showing evidence of a membranous VSD. Note the colour flow just below the aortic valve, this is the common location for membranous VSD.
- There is also trace aortic regurgitation.


- Short axis view at the level of the aortic valve demonstrating colour flow into the right ventricle.

- Zoomed apical 5 chamber demonstrating colour flow across the ventricular septum consistent with a membranous VSD.